
Rheumatoid Arthritis-Symptoms, Causes, Treatments & Diagnosis
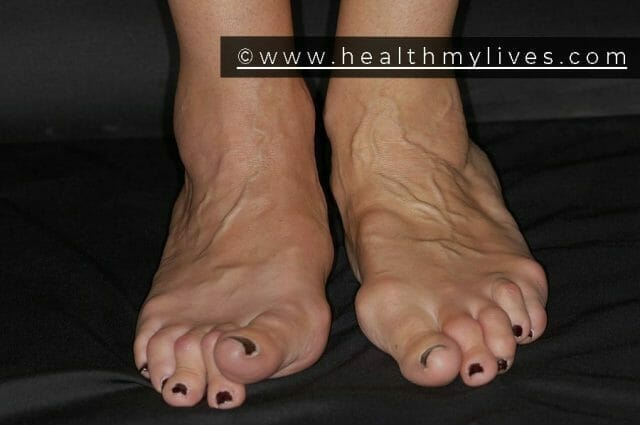
Contents
- Overview
- Arthritis or osteoarthritis?
- What are the symptoms of rheumatoid arthritis?
- Symptoms in the joints
- Other symptoms
- What are the causes of rheumatoid arthritis?
- Risk factors of rheumatoid arthritis
- What could be the complications of rheumatoid arthritis?
- Diagnosis
- History of rheumatoid arthritis
- Physical examination of rheumatoid arthritis
- Laboratory tests
- X-ray
- How is rheumatoid arthritis treated?
- Lifestyle
- Drugs
- Surgery
- Continuous monitoring and care
- Optional and reciprocal treatments
- Sources
Overview
Rheumatoid arthritis (RA) is an inflammatory disease that causes pain, swelling, stiffness and loss of function in the joints.
It is an autoimmune disease. The immune system, which normally defends the body against germs, attacks the lining of the joints by mistake.
RA can range from mild to severe. In most people it is a lifelong (chronic) condition.
Many people have periods of mild disease broken up by flares, when symptoms get worse. In others, symptoms are constant.
Arthritis or osteoarthritis?
Rheumatoid arthritis and osteoarthritis both affect the joints, and some symptoms overlap:
- Pain.
- Stiffness.
- Limited movement.
But the causes are very different.
RA is an autoimmune, inflammatory disease that can start at any age. Osteoarthritis is caused by wear and breakdown of joint cartilage and is most common later in life.
There are many other forms of arthritis, including:
- Gouty arthritis (gout).
- Septic arthritis.
- Psoriatic arthritis.
- Reactive arthritis.
This article focuses on rheumatoid arthritis.
What are the symptoms of rheumatoid arthritis?
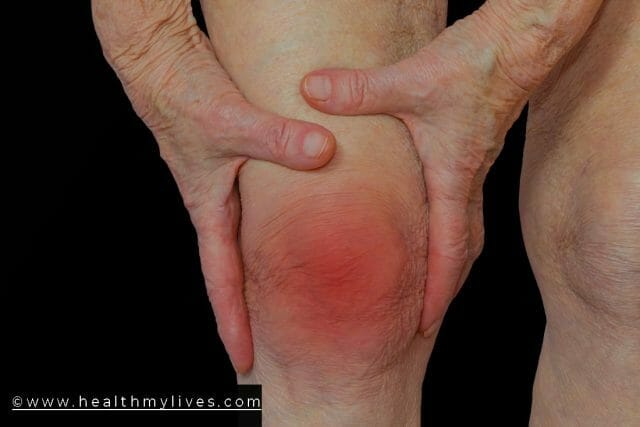
Symptoms usually develop slowly over several weeks, but in some people they come on quickly over a few days.
The main symptoms of rheumatoid arthritis are:
- Joint pain.
- Swelling.
- Joint stiffness.
RA can also cause general symptoms and inflammation in other parts of the body.
Symptoms vary from person to person, come and go, and can change over time.
Symptoms in the joints
RA can affect any joint, but it most often starts in the small joints of the hands, wrists and feet.
It usually affects joints on both sides of the body in a symmetrical pattern. For example, if your right hand is affected, your left hand often is too.
The main joint symptoms are:
- Pain: Joints hurt both at rest and when moving, and they are often tender to the touch.
- Stiffness: Joints feel stiff, especially in the morning or after resting. You may not be able to fully bend your fingers or make a fist. Morning stiffness from osteoarthritis usually eases within about 30 minutes, while stiffness from RA usually lasts longer.
- Swelling, warmth and redness: Inflamed joints become swollen, warm and painful to touch. Some people develop rheumatoid nodules, firm lumps under the skin, usually near the hands and elbows.
Other symptoms
Some people with RA also have general symptoms, such as:
- Fatigue and lack of energy.
- Low-grade fever.
- Sweating.
- Loss of appetite.
- Weight loss.
Inflammation from RA can also affect other parts of the body:
- Dry eyes and dry mouth.
- Chest pain or shortness of breath, if the heart or lungs are involved.
Key signs that point toward rheumatoid arthritis include:
- Tender, warm, swollen joints.
- The same joints affected on both sides of the body.
- Frequent involvement of the wrists and the finger joints closest to the hand.
- Morning stiffness lasting more than 30 minutes.
- Fatigue and occasional low-grade fever.
- Symptoms lasting six weeks or longer.
What are the causes of rheumatoid arthritis?
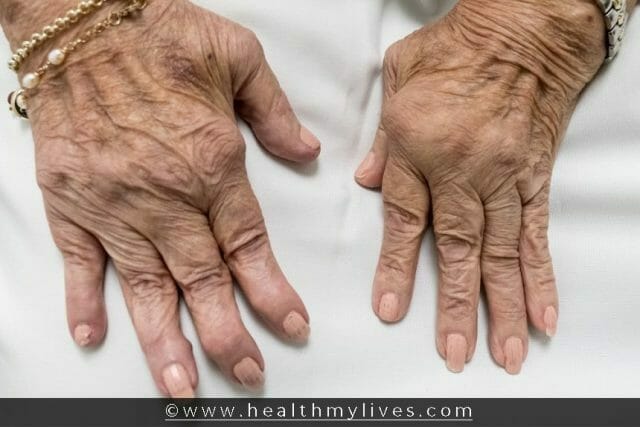
RA is mainly a disease of the joints. It is more common in women: the NIAMS reports that about two to three times as many women as men have it.
A joint is where two or more bones meet. Most joints let bones move and absorb shock when you walk or move.
The ends of the bones are covered with cartilage, a smooth, tough tissue.
A capsule surrounds the joint to protect and support it.
The capsule is lined with a thin tissue called the synovium. It makes synovial fluid, which lubricates and nourishes the joint.
In RA, the immune system attacks the joint tissues for reasons that aren't fully understood.
White blood cells move into the synovium and cause inflammation (synovitis), which shows up as:
- Warmth.
- Redness.
- Swelling.
- Pain.
These are the typical symptoms of rheumatoid arthritis.
The inflamed synovium thickens and makes the joint swollen, tender and sometimes warm to the touch.
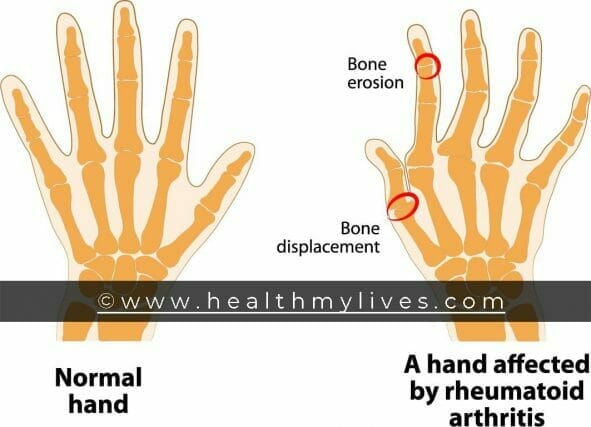
Over time, the inflamed tissue can damage cartilage and bone inside the joint.
The muscles, ligaments and tendons that support the joint can weaken and stop working as well.
This leads to the pain and joint damage seen in RA.
Joint damage can begin early in the disease, which is why early diagnosis and treatment are so important.
Risk factors of rheumatoid arthritis
Researchers don't fully know why the immune system turns on the joints, but several factors play a role.
Genetic (hereditary) factors: Certain genes that affect how the immune system works are linked to RA.
Each of these genes on its own only slightly increases risk.
Some people with these genes never develop the disease.
This shows that genes are not the only factor.
More than one gene may help decide who gets RA and how severe it becomes.
Environmental factors: Researchers believe something in the environment may trigger RA in people who are genetically at risk. Long-term smoking is the best-known trigger. Gum disease, lung disease and some infections may also play a role.
Other: Obesity may raise the risk. Hormones may also be involved, based on these observations:
- Women are more likely than men to get RA.
- The disease may improve during pregnancy and flare after delivery.
Researchers think hormones may contribute when genetic and environmental factors are also present.
There is no single cause. RA results from several factors working together.
What could be the complications of rheumatoid arthritis?
RA affects everyone differently. Some people have mild or moderate disease, with flares and periods of improvement (remission).
Others have severe, almost always active disease that can cause serious joint damage and disability, especially without effective treatment.
RA affects more than the joints. Many people also deal with:
-
Anxiety.
-
Feelings of helplessness.
-
Low self-esteem.
The disease can affect work, family life and plans such as having children.
Fortunately, modern treatment allows many people with RA to lead active, productive lives.
Treatment combines medicines that relieve pain and slow joint damage, a balance of rest and exercise, and education and support programs.
Research continues to improve treatment.
Some people with RA have problems outside the joints. Anemia (low red blood cell count) is common. Others include neck pain and dry eyes and mouth. In some patients, doctors see:
- Carpal tunnel syndrome.
- Inflammation that can affect the:
- Lungs (with cough, shortness of breath).
- Heart (pericarditis).
- Eyes and mouth (Sjogren’s syndrome), which causes dryness.
- Blood vessels (vasculitis).
- A higher risk of heart disease, including atherosclerosis.
Diagnosis
Rheumatoid arthritis can be hard to diagnose early, for several reasons:
- There is no single test for the disease.
- Symptoms differ from person to person and can look like other types of arthritis.
- It can take time to rule out other conditions.
- Symptoms often develop gradually and may be mild at first.
- So doctors use several approaches together to make the diagnosis.
History of rheumatoid arthritis
The doctor asks about your symptoms, when they started and how they have changed.
The doctor also asks about your medical history, your family's history and any medicines you take.
Clear answers help with the diagnosis and show how the disease affects your daily life.
Physical examination of rheumatoid arthritis
The doctor checks your reflexes, muscle strength and general health. They examine painful joints and watch how you walk, bend and do daily tasks.
They may also check your skin for nodules or rashes and listen to your chest for signs of lung inflammation.
Laboratory tests
Several blood tests help confirm RA. The most common are:
- Rheumatoid factor (RF): An antibody found in the blood of many people with RA. Not everyone with RA tests positive, and some people with a positive test never develop RA. RF can also be positive in other conditions. In someone with typical symptoms, a positive result supports the diagnosis. High levels are linked to more severe disease.
- Anti-CCP antibodies: This test detects anti-cyclic citrullinated peptide antibodies. It is positive in many people with RA and can be positive years before symptoms start. Used together with RF, it is very helpful for diagnosis.
- Other tests: A complete blood count checks for anemia, which is common in RA. The erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) measure inflammation. They help with diagnosis and with tracking how well treatment works.
X-ray
X-rays show how much joint damage has occurred.
They may look normal early in RA, before damage is visible, but they help rule out other causes of joint pain. Later, they help track how the disease progresses. Ultrasound or MRI can detect early changes that X-rays miss.
How is rheumatoid arthritis treated?

There is no cure for RA, and there is no proven way to prevent it, though not smoking lowers your risk. Treatment uses several approaches, combined and adjusted to each patient.
Whatever the treatment, the goals are the same:
- Relieve pain.
- Reduce inflammation.
- Slow or stop joint damage.
- Improve well-being and the ability to do daily tasks.
Effective treatment depends on a good relationship between patient and doctor. Trust helps make sure exercise, pain management and medicines are used the right way.
Support is also important for patients facing decisions about surgery.
Treatment approaches include:
- Lifestyle.
- Drugs.
- Surgery.
- Continuous monitoring and care.
Lifestyle
Healthy habits can help people with RA stay independent and positive.
Rest and exercise:
People with RA need a balance of rest and exercise: more rest when the disease is active, more exercise when it is calm. Rest eases inflamed joints and fatigue.
Short, frequent rests usually work better than long periods of bed rest.
Exercise keeps muscles strong and joints flexible.
It can also improve sleep, ease pain, lift your mood and help you keep a healthy weight.
Exercise programs should fit your abilities, limits and needs, which change over time.
Joint Care:
Some people find that wearing a splint for a short time eases pain and swelling by supporting and resting the joint.
Splints are used mainly on the wrists and hands, and sometimes the ankles and feet. A doctor, physical therapist or occupational therapist can help choose and fit one.
Self-help devices, such as zipper pullers and long-handled shoehorns, plus aids for getting in and out of chairs, the toilet and bed, can reduce stress on joints.
Stress reduction:
People with RA face emotional as well as physical challenges.
Fear, anger and frustration, along with pain and physical limits, can raise stress. Stress may also trigger flares in some people.
Stress can also affect how much pain you feel. Many techniques can help.
Regular rest, relaxation, distraction and visualization exercises can help. So can exercise programs, support groups and good communication with your healthcare team.
Diet:
No specific diet cures RA, but a balanced diet with enough (not excessive) calories, protein and calcium is important.
Some medicines affect how much alcohol you can safely drink. People taking methotrexate are usually told to avoid or strictly limit alcohol, because both can harm the liver.
Some research suggests a Mediterranean-style diet, rich in fish, vegetables, fruits, whole grains and olive oil, may be linked to a lower risk of RA, but the evidence is not conclusive.
A healthy diet also lowers the risk of heart disease and obesity, which are more common in people with RA.
Climate:
Some people say their joints feel worse when the weather changes suddenly, but there is no proven way to prevent this.
Moving to a different climate generally makes no difference to the long-term course of the disease.
Drugs
Most people with RA take medicine. Some medicines (analgesics) relieve pain. Others, such as corticosteroids and NSAIDs (nonsteroidal anti-inflammatory drugs), reduce inflammation but don't prevent joint damage on their own.
Disease-modifying antirheumatic drugs (DMARDs) slow the progression of the disease. According to MedlinePlus, early DMARD treatment is recommended for everyone with RA.
DMARDs include methotrexate, the most commonly used, plus hydroxychloroquine, leflunomide and sulfasalazine. Biologic DMARDs are often added when these don't work well enough.
Biologics are made using living cells. They block specific parts of the immune system that drive inflammation and joint damage.
Biologics approved for RA include abatacept, adalimumab, anakinra, certolizumab, etanercept, golimumab, infliximab, rituximab and tocilizumab.
Another option is a class of pills called JAK inhibitors, such as tofacitinib, baricitinib and upadacitinib. They are usually used for people who haven't responded well to TNF-blocking biologics.
Doctors used to start with aspirin or other pain relievers and wait for the disease to worsen before using stronger drugs.
That approach has changed. Research shows that early treatment with DMARDs, often in combination, works better at limiting joint damage.
Anyone with persistent joint symptoms should see a doctor experienced in RA, usually a rheumatologist, to reduce the risk of damage.
Many RA medicines work by calming the immune system. Because the immune system also fights infections, these drugs can raise the risk of serious infections.
People with untreated RA also have a higher risk of some infections and cancers, so it is hard to separate the effect of the disease from that of the drugs. Regular monitoring is important.
Surgery
Several types of surgery can help people with severe joint damage.
The main goals are to reduce pain, improve how the joint works and make daily activities easier.
Surgery isn't right for everyone. The decision should come after a careful discussion between doctor and patient.
Together they consider the patient's overall health, the condition of the joint or tendon, and the benefits and risks of the procedure. Cost may also be a factor.
Continuous monitoring and care
Regular medical care is important to track the disease, check how well medicines work and watch for side effects.
This usually means regular doctor visits, blood and urine tests, other lab tests and X-rays.
People with RA should also talk with their doctor about preventing osteoporosis.
Osteoporosis is a condition in which bones become weak and break easily.
RA raises the risk of osteoporosis in both men and women, especially with corticosteroid treatment. Ask your doctor whether calcium, vitamin D or other bone treatments are right for you.
Optional and reciprocal treatments
Special diets, supplements and other complementary approaches have been suggested for RA.
According to the NCCIH, supplements containing omega-3 fatty acids (fish oil) may help relieve RA symptoms. For most other approaches, there is little good evidence.
Talk with your doctor about the benefits and limits of any alternative therapy before you start.
If your doctor agrees it is safe, it can be part of your treatment plan. But don't replace standard medical care with it.
Sources
- Rheumatoid Arthritis, NIAMS
- Rheumatoid arthritis, MedlinePlus
- Baricitinib, MedlinePlus
- Rheumatoid Arthritis: In Depth, NCCIH
